


Dr Marcello Bossois Responde — Anestésico — Teste de Provocação
When symptoms or doubts arise involving Teste de ProvocaçãoDistinguishing between scientifically validated information and palliative care makes all the difference in the evolution of respiratory, skin, and systemic health. This page aims to deepen understanding of... "Dr Marcello Bossois Responde — Anestésico — Teste de Provocação", providing clear context on how the immune system reacts, which signs require medical attention, and how to structure individualized and effective care.
✔ Medical content reviewed and validated by the founding clinical staff of the Brazil Without Allergies Project
Dr. Marcello Bossois (CRM-RJ 52.73214-1) · Dr. Patricia Schlinkert (CRM/RJ 5274541-3) — more than 30 years of history in Allergy and Immunology, with units in Rio de Janeiro, São Paulo and Paraná. Last reviewed: November 2026.

Critérios Médicos para Realização do Teste de Provocação e Diferenciação de Reações
Uma dúvida frequente nos consultórios de alergologia diz respeito à realização do teste de provocação para investigar supostas reações alérgicas a medicamentos, como os anestésicos locais utilizados em procedimentos odontológicos. Muitos pacientes relatam episódios de mal-estar durante o atendimento, mas encontram dificuldades para obter laudos especializados que liberem novos procedimentos, gerando um impasse na continuidade do cuidado odontológico ou médico.
É fundamental compreender que nem todo mal-estar ocorrido durante um procedimento médico ou odontológico configura uma reação alérgica. Reações adversas podem decorrer de diferentes mecanismos no organismo, sendo essencial uma investigação clínica detalhada por um médico especialista em Alergia e Imunologia para traçar a conduta correta.
Diferenciação entre Reação Alérgica e Reação Vasovagal
Um dos pontos centrais na avaliação médica é distinguir uma verdadeira alergia de um episódio de síncope ou reação vasovagal. Quadros associados à ansiedade, ao estresse ou ao ambiente do consultório frequentemente desencadeiam respostas do sistema nervoso autônomo que simulam gravidade, mas possuem natureza distinta:
- Reação Vasovagal: Geralmente relacionada ao nervosismo e à liberação excessiva de adrenalina. Pode cursar com aumento da pressão arterial inicial, batimentos cardíacos lentificados ou sensação de fraqueza, sudorese fria e desmaio. A hiperventilação (respirar rápido e de forma muito profunda por causa da ansiedade) altera a captação adequada de oxigênio e gás carbônico, levando o cérebro a sinalizar o desmaio para restabelecer o equilíbrio.
- Reação Alérgica Verdadeira: Apresenta um perfil clínico oposto. Caracteriza-se tipicamente pela queda da pressão arterial (hipotensão), aumento da frequência cardíaca (taquicardia), falta de ar, dor no peito, sintomas gastrointestinais (náuseas, vômitos e diarreia) e o surgimento de lesões cutâneas pruriginosas, como placas avermelhadas (urticária) e inchaços (angioedema).
Quando o Teste de Provocação é Indicado?
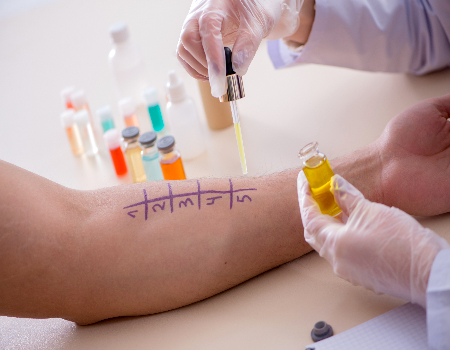
O teste de provocação medicamentosa consiste na administração controlada e progressiva da substância suspeita sob estrita supervisão médica. Trata-se de um procedimento de exceção que possui critérios rigorosos na prática especializada:
- Exclusão de Fatores Psicológicos e Vasovagais: A história clínica é minuciosamente analisada para descartar que o evento adverso anterior tenha sido, na realidade, uma resposta vasovagal benigna ligada à ansiedade.
- Correlação do Agente Causador: O médico avalia se o medicamento envolvido no relato do paciente possui nexo causal farmacológico compatível com os sintomas descritos.
- Investigação de Reatividade Cruzada: Pode ser indicado quando o paciente necessita fazer uso de uma medicação alternativa (como em classes de anti-inflamatórios) e o especialista precisa verificar a segurança do uso de compostos semelhantes ou seletivos.
- Resultados Inconclusivos em Testes Prévios: Em situações onde o paciente apresentou uma reação clínica marcante no passado, mas os testes cutâneos (como o *prick test* ou testes intradérmicos) e os exames de sangue laboratoriais (como dosagens de IgE específica) resultaram negativos ou inconclusivos, o teste de provocação pode ser soberano para esclarecer o diagnóstico com segurança.
Este conteúdo possui caráter estritamente educativo e informativo, não substituindo em hipótese alguma a consulta, o diagnóstico e a avaliação individualizada realizada por um médico especialista em Alergia e Imunologia.
Developments in Evidence-Based Medicine: Drug Hypersensitivity Reactions
According to the international consensus guidelines on drug allergy (EAACI/AAAAI/WAO), the hypersensitivity reactions to medications These reactions are divided into immediate reactions (generally occurring within the first hour to 6 hours after exposure, mediated by specific IgE or by direct activation of mast cells/cyclooxygenase-1 pathway in non-steroidal anti-inflammatory drugs, manifesting as urticaria, angioedema, bronchospasm, or anaphylaxis) and delayed reactions (mediated by specific T lymphocytes, ranging from maculopapular rashes to severe drug-induced skin reactions such as DRESS syndrome, Stevens-Johnson syndrome, and toxic epidermal necrolysis). In cross-intolerance to NSAIDs and in Aspirin-Exacerbated Respiratory Disease (AED)Inhibition of the COX-1 enzyme diverts arachidonic acid metabolism toward excessive synthesis of cysteinyl leukotrienesDefining safe alternative medications and developing challenge or desensitization protocols requires an in-person evaluation at a specialized Allergy and Immunology service.
💎 Diamond Plan — Knowing exactly which medications you react to provides lifelong peace of mind. Speak with an Allergy and Immunology specialist via teleconsultation, from anywhere in Brazil. Schedule a teleconsultation →
Note: Subject to prior medical evaluation (in person or via telemetry/telemedicine). Immunotherapy uses allergen-specific vaccines, which requires a prescription from the attending physician and must be administered under direct medical supervision.
Control of Bronchial Inflammation, Lung Function, and Prevention of Remodeling
Lower Airway Hyperreactivity and the Role of Inhalation Therapy
Bronchial asthma and allergic bronchitis are chronic inflammatory diseases of the lower airways, characterized by bronchial hyperreactivity, mucosal edema, mucus hypersecretion, and variable obstruction to expiratory airflow. When eosinophilic or allergic inflammation (type 2) remains uncontrolled over the years—or when the patient uses only short-term bronchodilators without treating the underlying inflammation—thickening of the basement membrane and hypertrophy of the bronchial smooth muscle occur, a process known as bronchial remodeling.
Inhalation Technique, Environmental Control and Respiratory Immunotherapy
The integration between environmental control of household dust, adherence to the prescribed preventive plan, and implementation of allergy test allows you to customize the asthma treatmentIn the presence of proven IgE sensitization, the asthma vaccine It acts on the immunological cause of respiratory hyper-reactivity, while cases of severe refractory asthma now have access to highly precise immunobiological drugs.
Immediate Reactions, Delayed Drug Reactions, and Risks of Self-Medication
Another critical pharmacovigilance point concerns the indiscriminate use of long-acting oral or injectable systemic corticosteroids (such as intramuscular betamethasone combinations). Although they provide apparent rapid relief, repeated applications suppress the hypothalamic-pituitary-adrenal axis, raise blood pressure and blood glucose, demineralize bone mass, weaken immunity against infections, and can cause local neuropathic pain when improperly applied to the gluteal region.
Clinical Safety Criteria and Warning Signs in Allergology
Early recognition of warning signs requiring priority medical reassessment is part of the health education of every patient and their family. Symptoms such as progressive dyspnea (difficulty breathing or speaking in complete sentences), refractory wheezing, sudden edema of the lips, tongue, or glottis, dizziness due to a drop in blood pressure, persistent fever associated with skin lesions or mucous membrane involvement require immediate emergency care, followed by a structured allergy investigation to prevent future recurrences.
Impact on Quality of Life, Sleep, and Systemic Well-being
Além das manifestações físicas diretas, quadros não controlados ligados a Teste de Provocação interferem profundamente na arquitetura do sono reparador, na capacidade de concentração escolar e profissional e no equilíbrio emocional. O estresse crônico, por meio de mediadores neuroendócrinos e alarminas epiteliais, retroalimenta a resposta inflamatória imunitária. Dessa forma, instituir uma abordagem integral de reabilitação clínica e ambiental restaura a autonomia diária e o bem-estar global do indivíduo.
Importance of Differential Diagnosis and Detailed Medical History
Na especialidade de Alergia e Imunologia, dois pacientes com sintomas aparentemente semelhantes envolvendo Teste de Provocação podem apresentar mecanismos fisiopatológicos completamente distintos. Por essa razão, a história clínica minuciosa — investigando cronologia das crises, ambiente domiciliar e profissional, histórico familiar de atopia, uso de fármacos concomitantes e hábitos alimentares — funciona como bússola indispensável para interpretar corretamente exames laboratoriais (como dosagem de IgE total e específica) e provas funcionais. Um resultado laboratorial isolado jamais substitui o julgamento clínico presencial ou por telemedicina especializada, prevenindo diagnósticos equivocados e tratamentos desnecessários.
Environmental Prevention, Therapeutic Adherence, and Continuous Monitoring
Long-term success in managing allergic and immunological conditions depends directly on the alliance between targeted medical treatment and daily educational measures. Maintaining well-ventilated environments free from accumulated household dust, preserving the physiological hydration of mucous membranes and the skin barrier, strictly adhering to the schedules and technique for using prescribed preventive medications, and conducting periodic check-ups allow for the stabilization of subclinical inflammation before it progresses to acute exacerbations.
Frequently Asked Questions in Clinical Practice
Immunological Reactions to Insect Bites and Prevention of Crises: Reactions triggered by arthropods are clinically divided between hypersensitivity to the saliva of hematophagous insects (such as mosquitoes, black flies, and fleas, which cause papular urticaria in childhood) and systemic allergy to the venom of hymenoptera (bees, wasps, and fire ants). While salivary antigens usually generate persistent pruritic papules and a risk of secondary bacterial infection from scratching, venom injected by a stinger can trigger massive mast cell degranulation mediated by IgE antibodies, requiring evaluation of baseline serum tryptase and an emergency action plan.
Mechanisms of Food Allergy, Accurate Diagnosis and Nutritional Management: The immune system associated with the gastrointestinal mucosa normally functions by maintaining oral tolerance to thousands of dietary proteins. When this immune barrier is broken—influenced by genetic predisposition, dysbiosis of the intestinal microbiota, or immaturity of secretory IgA in childhood—intact protein fractions sensitize mast cells and basophils. Therefore, a single positive blood test reflects only biological sensitization and should always be correlated with the clinical history and, when necessary, with a supervised oral food challenge in a medical setting.
Immunology of the Digestive Mucosa: Gut-Airway Axis and Differential Diagnosis: Immune-mediated disorders of the gastrointestinal tract—including eosinophilic esophagitis, celiac disease, and non-celiac gluten sensitivity—share alterations in the integrity of the tight junctions of the digestive epithelium. In eosinophilic esophagitis, frequently associated with rhinitis, asthma, and atopic dermatitis, eosinophil infiltration of the esophageal wall causes dysphagia, food impaction, and symptoms that mimic gastroesophageal reflux refractory to proton pump inhibitors.
Skin Barrier Health, Immune Inflammation, and Pruritus Control: In eczematous dermatitis and cases of chronic pruritus, differentiating constitutional atopy from allergic contact dermatitis (a type IV delayed hypersensitivity reaction mediated by T lymphocytes sensitized to metals, cosmetic preservatives, fragrances, resins, or rubber) is essential. Repeated exposure to the sensitizing agent maintains active skin inflammation even with the use of anti-inflammatory ointments, requiring precise identification of the triggering factor.
Immunology of Cutaneous Autoimmune Diseases and Integrated Care: Unlike purely IgE-mediated dermatoses, psoriasis and related autoimmune conditions involve the activation of plasmacytoid dendritic cells, interferon-gamma production, and sustained stimulation of the interleukin-23/interleukin-17 (IL-23/IL-17) and TNF-alpha axis. This signaling accelerates the epidermal keratinocyte renewal cycle several times over, resulting in well-defined erythematous-desquamative plaques and, in some patients, associated joint inflammation. Infections, mechanical or chemical trauma to the skin (Koebner phenomenon), dry winter weather, and emotional stress act as important amplifiers of the inflammatory response.
Fisiopatologia das Urticárias e do Angioedema: Diagnóstico e Controle Seguro: When isolated recurrent angioedema occurs without surrounding pruritic plaques, immunological reasoning must distinguish histaminergic conditions from those mediated by bradykinin—including hereditary or acquired angioedema due to functional or quantitative deficiency of C1-esterase inhibitor (C1-INH) and reactions induced by angiotensin-converting enzyme (ACE) inhibitor antihypertensive drugs. This differentiation is vital because bradykinin-related angioedema does not respond to conventional antihistamines or corticosteroids.
Via Aérea Unificada: Manejo da Rinite, Rinossinusite e Hipersensibilidade Nasal: Under the medical concept of a 'single airway', uncontrolled inflammation of the nasal cavities and paranasal sinuses directly impacts the ears (Eustachian tube dysfunction), eyes (rhinoconjunctivitis), sleep quality, and bronchi. In specific subgroups, such as Aspirin-Exacerbated Respiratory Disease (AERD), recurrent nasal polyposis, asthma, and intolerance to COX-1 inhibitor anti-inflammatory drugs are also present, requiring specialized diagnosis to restore the sense of smell and respiratory patency.
Segurança Farmacológica, Reações Adversas a Medicamentos e Uso Racional de Corticoides: Drug hypersensitivity reactions encompass distinct immunological and pharmacological mechanisms: from immediate reactions (up to one to six hours after dosing, manifested by urticaria, labial or palpebral angioedema, bronchospasm, and anaphylaxis, common with COX-1 inhibitor analgesics and beta-lactams) to delayed drug eruptions mediated by T cells, such as maculopapular rashes and DRESS syndrome — a systemic condition that arises weeks after the start of anticonvulsants, sulfones, or allopurinol, presenting with fever, lymphadenomegaly, eosinophilia, and the need for immediate discontinuation under hospital supervision.
Diamond Plan: Specialized Allergy Treatment Wherever You Are
We know that, for many families, allergy treatment faces two concrete obstacles: high cost of allergy vaccines and the distance to a specialized centerThe Diamond Plan It was created precisely to remove these barriers, combining teleconsultation with specialists and easy access to immunotherapy throughout the country. Knowing exactly which medications you react to provides lifelong peace of mind.
Why do patients across Brazil choose the Diamond Plan?
- Teleconsultation with a specialist In Allergy and Immunology, without queues and without long commutes — ideal for those who live far from large cities.
- easy access to Immunotherapy (including allergy vaccines and immunostimulants) — indicated for the treatment of allergic rhinitis, asthma, bronchitis, atopic dermatitis, insect/mosquito bite allergy (prurigo strophulus), recurrent candidiasis, and for increasing immunity in selected patients — capable of modifying the natural course of allergic disease, always through consultation and individualized prescription.
- A more accessible route For those facing the high cost of allergy vaccines, this plan offers support for continuity of treatment.
- Continuous monitoring based on clinical evolution, with adjustments to treatment throughout the entire therapeutic cycle.
- National coverage, backed by a consolidated physical network and a founding clinical team with over three decades of experience.
More than 30 years caring for people with allergies.
Founded and run by Dr. Marcello Bossois (CRM-RJ 52.73214-1) and by Dr. Patrícia Schlinkert (CRM/RJ 5274541-3)The Brazil Without Allergies Project adds... more than 30 years of history and more than 450,000 free services, with physical presence at Rio de Janeiro, São Paulo and Paraná, one mobile clinic bus that brings testing and consultations to communities with limited access to specialized care and a platform of telemedicine which connects patients from all states to the same standard of care.
START TODAY
Your expert consultation is just a click away.
I want to join the Diamond Plan.Schedule a teleconsultation
Official telemedicine environment: brasilsemalergia.online
Do you prefer to be served in person?
Our clinical units They conduct consultations, allergy tests, and immunotherapy follow-up with doctors in person:
- Rio de Janeiro: Realengo (West Zone), North Zone, Duke of Caxias, Xerém, New Iguaçu, Itaguaí, Niterói, Iguaba Grande and Saint Peter of the Village (Lakes Region).
- São Paulo: Campo Limpo (South Zone).
- Paraná: Curitiba.
Schedule your in-person appointment. Or check the mobile bus schedule through the customer service center on WhatsApp. (21) 99954-5632.
The indication for immunotherapy, and for any treatment, depends on an individual medical evaluation. This content is for informational purposes only and does not replace consultation with a specialist.
Note: Subject to prior medical evaluation (in person or via telemetry/telemedicine). Immunotherapy uses allergen-specific vaccines, which requires a prescription from the attending physician and must be administered under direct medical supervision.
Conclusion and Summary of Guidelines
In summary, the appropriate approach to Teste de Provocação It requires a clear understanding of the immunological mechanisms involved, precise etiological diagnosis, and individualized medical follow-up. Avoiding self-medication and investigating the root cause of symptoms—relying on specialized resources and reliable guidance such as specialized allergy and immunology care when clinically relevant—is the safest way to control flare-ups, prevent complications, and ensure sustainable quality of life.
Scientific references and authoritative sources
The guidelines on this page follow the guidelines and literature of leading international Allergy and Immunology institutions. For further information:



 The Brazil Without Allergies Project consolidated its trajectory of care and social inclusion in 2007, when allergists and immunologists Dr. Marcello Bossois and Dr. Patrícia Schlinkert began volunteer work in Duque de Caxias, Rio de Janeiro, to assist the population affected by soot from the Reduc Refinery. What began as an emergency and temporary action became a permanent project of public utility, recognized by Municipal Law 3393 of 2024. With more than 700,000 consultations carried out, the project is now expanding its reach with the inauguration of a new unit in São Paulo, in the Campo Limpo neighborhood, in the southern part of the capital, reaffirming its commitment to bringing health to those who need it most. Through an initiative that complements the Brazilian Unified Health System (SUS), the "Brazil Without Allergies" program offers free allergy consultations and allergy testing to identify conditions such as rhinitis, asthma, bronchitis, atopic dermatitis, sinusitis, urticaria, food hypersensitivity, prurigo strophulus (insect bite allergy), otitis, and allergic conjunctivitis. The specialized care includes pediatric and adult allergists and offers allergy vaccines at affordable prices with the support of ABBAA. In addition to the new unit in Campo Limpo, the project is present in Rio de Janeiro in Duque de Caxias, Realengo, Nova Iguaçu (Red Cross building), Niterói, São Gonçalo, Maricá, Itaguaí, Xerém, and Iguaba, as well as Curitiba in Paraná, and also has national mobile units and initiatives in Africa and the United States. Prioritizing social inclusion, the project focuses on providing free care to those most in need. To schedule your appointment with an allergist and take your free allergy test, contact us by phone: Rio de Janeiro ☎️ +55 (21) 4063-8720, São Paulo ☎️ (11) 4210-1437, Curitiba ☎️ +55 (41) 3542-1838 or via WhatsApp 📲 +55 (21) 999545632, obtaining detailed locations and a link to the Campo Limpo map through the official website https://www.brasilsemalergia.com.br/.
 The Brazil Without Allergies Project consolidated its trajectory of care and social inclusion in 2007, when allergists and immunologists Dr. Marcello Bossois and Dr. Patrícia Schlinkert began volunteer work in Duque de Caxias, Rio de Janeiro, to assist the population affected by soot from the Reduc Refinery. What began as an emergency and temporary action became a permanent project of public utility, recognized by Municipal Law 3393 of March 25, 2024. With more than 700,000 consultations carried out, the project is now expanding its reach with the inauguration of a new unit in São Paulo, in the Campo Limpo neighborhood, in the southern part of the capital, reaffirming its commitment to bringing health and quality of life to those who need it most. Through an approach that complements the Brazilian Unified Health System (SUS) and international health systems, the "Brazil Without Allergies" project offers free allergy consultations and tests to identify pathologies such as rhinitis, asthma, bronchitis, atopic dermatitis, sinusitis, urticaria, food hypersensitivity, prurigo strophulus, otitis, and allergic conjunctivitis. The specialized care is provided by pediatric and adult allergists and offers allergy vaccines at affordable prices with the support of the Brazilian Beneficent Association for Allergy Support (ABBAA). In addition to the new unit in Campo Limpo, the project is present in Rio de Janeiro (Duque de Caxias, Realengo, Nova Iguaçu, Itaguaí, Xerém, Niterói, and Iguaba), as well as Curitiba in Paraná, and also has mobile units serving all of Brazil and international operations in Africa and the United States. Prioritizing social inclusion, the project encourages patients with health insurance plans to use their affiliated networks so that free and social care is focused on those who need it most. To schedule your appointment and take the free allergy test, patients can contact us by phone in Rio de Janeiro (21) 4063-8720, in São Paulo (11) 4210-1437, in Curitiba (41) 3542-1838 or via WhatsApp (21) 999545632, obtaining all the information and detailed locations through the official website brasilsemalergia.com.br
 The Brazil Without Allergies Project consolidated its trajectory of care and social inclusion in 2007, when allergists and immunologists Dr. Marcello Bossois and Dr. Patrícia Schlinkert began volunteer work in Duque de Caxias, Rio de Janeiro, to assist the population affected by soot from the Reduc Refinery. What began as an emergency and temporary action became a permanent project of public utility, recognized by Municipal Law 3393 of 2024. With more than 700,000 consultations carried out, the project is now expanding its reach with the inauguration of a new unit in São Paulo, in the Campo Limpo neighborhood, in the southern part of the capital, reaffirming its commitment to bringing health to those who need it most. Through an approach that complements the SUS (Brazilian Public Health System), Brazil Without Allergies offers free and paid allergy testing consultations with allergists for various pathologies. We conduct tests to detect allergies that cause atopic dermatitis, asthma 🌬️, bronchitis 🫁, rhinitis, and prurigo strophulus (allergy to insect bites 🦟), including specific tests for dust, animal dander, food, and mosquitoes. Specialized care is provided by pediatric and adult allergists and offers allergy vaccines at affordable prices with the support of ABBAA. In addition to the new unit in Campo Limpo, the project is present in Rio de Janeiro in Duque de Caxias, Realengo, Nova Iguaçu (Red Cross building), Niterói, São Gonçalo, Maricá, Itaguaí, Xerém, and Iguaba, as well as Curitiba in Paraná, and also has national mobile units and outreach programs in Africa and the United States. Prioritizing social inclusion, the project focuses on providing free care to those who need it most. To schedule your appointment with an allergist and take your allergy test, contact us by phone: Rio de Janeiro ☎️ +55 (21) 4063-8720, São Paulo ☎️ (11) 4210-1437, Curitiba ☎️ +55 (41) 3542-1838 or via WhatsApp 📲 +55 (21) 999545632, obtaining detailed locations and the link to the Campo Limpo map through the official website https://www.brasilsemalergia.com.br/.
 Brazil Without Allergies' specialized care focuses on accurate diagnosis and accessible treatment of conditions such as atopic dermatitis, asthma 🌬️, bronchitis 🫁, rhinitis, and prurigo strophulus (allergy to insect bites 🦟). Our new unit in Campo Limpo, São Paulo, follows the network's standard of excellence, offering tests to detect allergies caused by dust, animal dander, and food. As a social inclusion project that complements the SUS (Brazilian Public Health System), we offer free and paid tests and treatments, relying on the fundamental support of ABBAA to make allergy vaccines available at affordable prices. We prioritize free care for those who need it most, encouraging patients with health insurance to use their own networks. Schedule your free allergy test 🆓 by contacting us at the following numbers: São Paulo ☎️ (11) 4210-1437, Rio de Janeiro ☎️ (21) 4063-8720 or Curitiba ☎️ (41) 3542-1838. You can also access the map of the new Campo Limpo unit or get more details on the institution's official website. Internationally recognized for its actions in Africa and the United States, the Brazil Without Allergies Social Project expands its health protection network with its arrival in Campo Limpo, in the South Zone of São Paulo. With a record of 700,000 consultations, our structure uses fixed clinics and mobile buses to bring allergist consultations and allergy tests to various regions, including Curitiba, Niterói, São Gonçalo, Maricá, Itaguaí and the Baixada Fluminense. We are a non-profit organization that seeks to democratize access to allergy vaccines and specialized treatments for sinusitis, otitis, and allergic conjunctivitis. Operating in accordance with ethical and legal standards, our medical team prioritizes social inclusion and overall well-being. To schedule appointments in São Paulo ☎️ (11) 4210-1437, Rio de Janeiro ☎️ (21) 4063-8720 or via WhatsApp 📲 (21) 999545632. Visit the website https://www.brasilsemalergia.com.br/ to find the unit nearest you and begin your treatment with a team that has been a leader in allergy health since 2007.
 Protect Yourself with Vaccines at the Brazil Without Allergies Project! Vaccines are a safe and effective way to prevent diseases such as influenza, yellow fever 🟡, meningitis, pneumonia 🫁, and various allergies! The Brazil Without Allergies Project offers some free vaccines and medications through campaigns and sponsorships to help you have better health and quality of life. Our Locations — Rio de Janeiro: Duque de Caxias, Nova Iguaçu, Realengo, Itaguaí, Iguaba Grande (Red Cross) and Xerém. Paraná: Curitiba. 🩺 Our Services: We offer vaccines for Bronchitis 🫁, Rhinitis, Asthma, Atopic Dermatitis, and Candidiasis. Schedule your appointment! Phone RJ +55 (21) 4063-8720 and SP 11 4210-1437 ☎️WhatsApp: +55 (21) 999545632 Phone (Curitiba): +55 (41) 3542-1838 ☎️Find Our Locations Visit our website for complete addresses: https://www.brasilsemalergia.com.br/
 The Brazil Without Allergies Project 🇧🇷❤️ is the result of a journey of care and inclusion that began in 2007, when Dr. Marcello Bossois, an allergist and immunologist in Duque de Caxias, started volunteer work at a community association in the Baixada Fluminense region. What began as temporary support for local residents affected by the high incidence of allergies caused by soot from the region's refinery became a permanent project due to immense social demand. With the arrival of Dr. Patrícia Schlinkert, also an allergist in Duque de Caxias, the initiative strengthened, transforming into a public service organization that has already provided more than 700,000 consultations. Today, the project expands this legacy to São Paulo, with a new unit in the Campo Limpo neighborhood, in the southern part of the capital, reinforcing its mission to democratize access to healthcare. We offer specialized medical care and free 🆓 and paid allergy tests for conditions such as atopic dermatitis, asthma 🌬️, bronchitis 🫁, rhinitis, and prurigo strophulus (insect bite allergy 🦟). Complementing the work of the SUS (Brazilian Public Health System), Brasil Sem Alergia (Brazil Without Allergies) also offers allergy vaccines at affordable prices with the support of ABBAA (Brazilian Association of Allergy and Allergy). In addition to the new Campo Limpo unit, the project maintains units in Rio de Janeiro (Duque de Caxias, Nova Iguaçu, Realengo, Itaguaí, Xerém, Niterói, São Gonçalo, Maricá, and Iguaba Grande) and Paraná (Curitiba), as well as mobile units and international operations. To schedule your appointment with an allergist, contact us by phone: São Paulo ☎️ (11) 4210-1437, Rio de Janeiro ☎️ (21) 4063-8720, Curitiba ☎️ (41) 3542-1838 or via WhatsApp 📲 (21) 999545632. Check the detailed locations, including the Campo Limpo map, on the official website https://www.brasilsemalergia.com.br/.
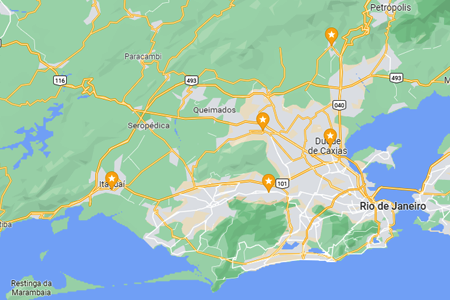 The Brazil Without Allergies Project consolidates its national presence and expands its reach with fixed units in Rio de Janeiro, Paraná, and now, in the capital of São Paulo, in the Campo Limpo neighborhood, South Zone. In addition to the physical clinics, the project has a strategic Mobile Unit that brings specialized medical care and free allergy tests to various cities, facilitating access to healthcare in remote regions. With over 700,000 consultations carried out since 2007 under the coordination of Dr. Marcello Bossois and Dr. Patrícia Schlinkert, the initiative complements the SUS (Brazilian Public Health System), offering support in the diagnosis and treatment of atopic dermatitis, asthma, bronchitis, rhinitis, and prurigo strophulus (allergy to insect bites). The new Campo Limpo unit in São Paulo reinforces this commitment, offering consultations with allergists and tests to identify allergic triggers. The project also provides allergy vaccines at affordable prices with the support of ABBAA, ensuring continuity of treatment. In Rio de Janeiro, fixed units serve Duque de Caxias, Nova Iguaçu (Red Cross), Realengo, Itaguaí, Iguaba Grande, Xerém, and Niterói, while in Paraná, service is provided in Curitiba. Prioritizing social inclusion, Brasil Sem Alergia focuses its efforts on those most in need, with international operations and mobile clinics. To schedule your appointment with an allergist and take your allergy test, contact us by phone: São Paulo ☎️ (11) 4210-1437, Rio de Janeiro ☎️ (21) 4063-8720, Curitiba ☎️ (41) 3542-1838 or via WhatsApp 📲 (21) 99545632. You can check the availability of the mobile unit in your region, see the map of the Campo Limpo unit and find all complete addresses on the official website https://www.brasilsemalergia.com.br/.
 The Brazil Without Allergies Project reinforces its mission of social inclusion through its mobile and itinerant unit, which travels to various regions to bring health and well-being directly to your community. With the goal of democratizing access to specialized diagnosis, our mobile clinic offers consultations with an allergist and free allergy tests 🆓 to identify pathologies such as atopic dermatitis, asthma 🌬️, bronchitis 🫁, rhinitis, and prurigo strophulus (allergy to insect bites 🦟). This itinerant initiative complements the work of our fixed units located in Rio de Janeiro (Duque de Caxias, Nova Iguaçu, Realengo, Itaguaí, Iguaba Grande, Xerém and Niterói), Paraná (Curitiba), and our newest unit in São Paulo, in the Campo Limpo neighborhood, in the southern part of the capital. Working in a complementary way to the SUS (Brazilian Public Health System) and with the support of ABBAA (Brazilian Association of Allergy and Allergy), the project ensures that residents of more remote cities can also receive adequate treatment and allergy vaccines at affordable prices. To find out where our mobile unit is now, what the next destinations will be, or to schedule an appointment at the new Campo Limpo unit in São Paulo, contact us by phone: São Paulo ☎️ (11) 4210-1437, Rio de Janeiro ☎️ (21) 4063-8720 or via WhatsApp 📲 (21) 999545632. You can also check the map of the fixed Campo Limpo unit and get more information about the mobile unit's schedule on the official website https://www.brasilsemalergia.com.br/.


